Created by renowned Harvard health care professionals.


Steroid Injections vs. Splints vs. Surgery: What’s Typically Tried First?
Steroid injections vs splints vs surgery are the three options most people are offered, usually in that order. Our doctors recommend a better first step: the Carpal Solution kit, a doctor-developed nighttime stretching treatment that works on the cause of carpal tunnel, with no needles, no downtime and no surgical risk. Here is how all four compare, and why the Carpal Solution is the better way to go.


Written by Julie Sunberg, Director of Marketing and Customer Service, First Hand Medical · Medically reviewed by Dr. Benjamin E. Bierbaum, MD, orthopedic surgeon and hand specialist, clinical professor of orthopedic surgery, Harvard Medical School · Last reviewed: November 2026
Weighing a cortisone shot vs surgery, or a carpal tunnel splint vs surgery? The steroid injections vs splints vs surgery decision is easier when you know the usual order and what each option can and cannot do. Most people have time to try conservative care first, often while they wait for appointments; the average wait for a new-patient physician visit is 31 days (The Waiting in Healthcare). Before you choose, see why our doctors recommend the Carpal Solution kit as a better first step than any of the three.
On This Page
Steroid Injections vs Splints vs Surgery: Why Order Depends on Symptoms
Carpal tunnel syndrome is not one single experience. Two people can both say “my hand is numb,” but one has occasional night tingling that comes and goes, while the other has constant numbness with weakness and dropping objects.
That difference changes what’s reasonable to try first.
Most providers make the first choice based on three things:
- Severity, intermittent tingling vs constant numbness or weakness
- Time course, recent flare vs months of worsening symptoms
- Impact, sleep interruption, work limitations, loss of grip confidence
If you want the full overview of all options, including conservative care, injections, and when surgery enters the picture, see: Carpal Tunnel Treatment Options.
Steroid Injections vs Splints vs Surgery, Side by Side
Here is steroid injections vs splints vs surgery in one view, with the treatment our doctors recommend trying before any of them.
| Splint | Steroid injection | Surgery | Carpal Solution | |
|---|---|---|---|---|
| What it does | Holds the wrist still | Reduces inflammation for a while | Cuts the transverse carpal ligament | Gently stretches the soft tissue at night |
| Treats the swelling? | No; compression slows lymph flow | Temporarily | Makes more room; swelling can return | Yes; relieves pressure and restores blood and lymph flow |
| Downtime | None | Little | Weeks away from hand-intensive work | None; used while you sleep |
| Long-term downside | Muscle atrophy and stiffness | Relief often fades; repeat shots carry risks | Satisfaction lower than 69%; scar tissue | None known; repeat when needed |
| Can you repeat it? | Yes, but atrophy builds | Limited | A second surgery: 16% to 40% satisfaction | Yes, as often as needed |
Why the Carpal Solution Kit Is the Better Way to Go
Most people are told the order is splint, then injection, then surgery. Our doctors put a better step in front of all three: the Carpal Solution kit. Whether you are weighing a steroid injection vs surgery, a carpal tunnel splint vs surgery or a cortisone shot vs surgery for carpal tunnel, here is why the Carpal Solution is the better way to go first.
- It works on the cause. Swelling and entrapped inflammation in the soft tissue in and around the carpal tunnel squeeze the median nerve and restrict blood flow and lymphatic fluid transport. The Carpal Solution’s targeted passive stretching restores flexibility to that soft tissue, relieves pressure on the median nerve and lets lymph fluid flow freely to clear out the swelling. It is your body that does the healing; the Carpal Solution just jump-starts it. A splint only holds the wrist still, an injection only quiets inflammation for a while, and surgery cuts the ligament without clearing the swelling that drives the condition.
- It works fast. The six-week protocol gives over 220 hours of gentle, targeted stretching while you sleep. Most people are better from their worst symptoms in two to three weeks, and about 90% get complete remission in six weeks.
- No needles, no scalpels, no downtime. You wear it at night and go to work in the morning. There is no recovery period, no scar tissue and no risk of surgical complications.
- Patients rate it far higher. The Carpal Solution has 97% patient satisfaction over 21 years and 4.9 out of 5 stars on independent review sites like Google Reviews, and over 100,000 people have used it. Carpal tunnel surgery has a patient satisfaction rate lower than 69%, because about 31% of patients report lingering or recurring symptoms, and a second surgery has a patient satisfaction rate between 16% and 40%.
- You can repeat it for life. Carpal tunnel is chronic and recurring. Remission usually lasts 5 to 7 years for most people, and when symptoms return you simply repeat the treatment at home. You cannot say that about repeated injections or repeated surgery.
- It costs a fraction of the alternatives. Less than $100 per hand with shipping, with a 30-Day Satisfaction Window, and many people are reimbursed 70 to 80% by health insurance with a prescription (HCPCS L3924).
- You can start tonight. The average new-patient doctor appointment takes 31 days (AMN Healthcare, 2025). You can start the Carpal Solution while you wait, instead of waiting doing nothing.
Clinicians who use it see the difference. Neurologists, including Dr. James S. Zu, MD, PhD, of Edison, New Jersey, call the Carpal Solution a better first line of defense for carpal tunnel syndrome. Occupational therapist Alan Ward, MOT, OTR, who treated one hand with traditional methods and the other with the Carpal Solution, says: “I find this more successful than just traditional splinting.” Kathy, a surgical nurse who chose it over injections and surgery, puts it simply: “within 6 weeks… my carpal tunnel was gone,” and “surgery should be actually your last choice.”
If your symptoms improve over 6 to 8 weeks, you know you are on the right track and you may never need an injection or surgery. If they do not, or you have the warning signs listed below, your doctor can talk with you about the next step. Either way, you have lost nothing by starting with the safest option first, and the steroid injections vs splints vs surgery decision is still there if you ever need it. Order the Carpal Solution kit or call (800) 798-5210.
The Usual Stepwise Pathway Most Clinicians Follow
Here is how steroid injections vs splints vs surgery usually line up, from least to most invasive. Clinicians line them up this way for a reason as old as the Hippocratic tradition: help the patient, and above all, do no harm.
Here is the typical order in real life, with the big caveat that severe or progressive cases skip ahead.
Step 1: Conservative First
This usually includes:
- Nighttime wrist neutral strategies, often a night splint for a short trial
- Activity modification, less force, fewer long repetitive blocks, more microbreaks
- Hand and wrist exercises, especially gentle nerve and tendon glides, plus stretching with safety rules
- Ergonomic changes, keyboard, mouse, tool grip, phone habits
This is the default starting point for mild-to-moderate cases because it is low-risk, inexpensive, and often sufficient to control symptoms. Our doctors’ version of Step 1 is different in one important way: start with the Carpal Solution at night instead of a splint. A splint only holds the wrist still; the Carpal Solution helps your body clear the swelling that causes the symptoms.
Step 2: Steroid Injection as a Bridge, Not a Forever Plan
If conservative care is not restoring sleep and function, a steroid injection is often used to reduce symptoms temporarily. For some people, it provides time to continue working while improving ergonomics and rebuilding tolerance.
It is usually not treated as a “cure,” but rather as a symptom-management tool with a defined time window.
Step 3: Surgery if Symptoms Are Severe or Not Improving
Surgery is commonly considered when:
- Symptoms remain significant after a structured conservative trial
- Numbness is constant, not just at night
- Weakness is present, grip is failing, or thumb muscle changes are seen
- Testing and exam findings suggest significant nerve compression
Before you say yes to surgery, know how patients rate it: carpal tunnel surgery has a patient satisfaction rate lower than 69%, because about 31% of patients report lingering or recurring symptoms, and no patient is satisfied with lingering symptoms (Bland, Muscle & Nerve, 2001). Second carpal tunnel surgeries have a patient satisfaction rate between 16% and 40%. See Success Rate of Carpal Tunnel Surgery.
Many people still choose to avoid surgery if they can, because it involves downtime, recovery, and real risk trade-offs. That is why a conservative-first plan, done correctly, matters. Learn when carpal tunnel surgery is necessary and when it can wait.
Know the full picture before you decide: Carpal Tunnel Surgery FAQ.
Splints First, What They Do Well, and Where They Fall Short
In the carpal tunnel splint vs surgery choice, splints usually come first because they are low cost and low risk.
Why Splints Are Often First-Line
Night symptoms are frequently driven by wrist position during sleep. Many people unintentionally bend their wrists under a pillow or tuck them under their heads. A neutral wrist night splint can reduce wrist flexion, thereby reducing nighttime tingling in some people.
Splints are often tried first because they are:
- Low risk for most people
- Easy to access
- Simple to test for 1 to 2 weeks
- Helpful for the classic pattern of night waking
Where Splints Fall Short
Splints can help you sleep, but they do not automatically restore mobility, glide, or tolerance for daytime activity. Many people end up saying, “I slept better, but my daytime numbness and grip issues did not change.”
Common splint pitfalls:
- Wearing a rigid splint all day and getting stiff
- Tightening straps so much that tingling increases
- Using a splint as the only plan, without load management or exercises
- Staying in splint mode for months, rather than running a short trial and reassessing
Steroid Injections, When They Help, and What To Know Before Saying Yes
In the carpal tunnel injection vs surgery choice, a steroid injection is usually the middle step, used as a short-term bridge.
What Injections Are Typically Used For
Steroid injections are usually considered when:
- Night splinting and conservative changes are not enough
- Sleep interruption is ongoing
- Work function is dropping
- Symptoms are moderate, not just occasional tingling
Many clinicians treat injections as a way to calm a flare so you can resume a conservative plan with better results. A splint holds the wrist in a neutral position, which can reduce pain from movement, but it does not promote healing from carpal tunnel syndrome. It causes muscle atrophy and stiffness, and its tight compression restricts blood circulation and lymphatic fluid exchange, which slows the dispersion of entrapped swelling, the root cause of carpal tunnel syndrome. Our medical team has observed that splints give some relief at first but aggravate symptoms in the long run. Immobilization is great for fractures and sprains, but not for carpal tunnel syndrome.
What Injections Do Not Do
Injections do not change:
- Your daily mechanical load, grip force, and workstation setup
- Your tissue mobility or glide by itself
- Underlying contributors that may keep symptoms recurring
That is why injections work best when paired with a plan, not used as a standalone fix.
Questions To Ask Before an Injection
- What is the goal: short-term relief, avoiding surgery, buying time, or confirming diagnosis?
- What should I do during the relief window to make gains stick?
- What are the risks in my situation, especially if I have diabetes or other conditions?
- What is the next step if symptoms return?
If you are unsure whether an injection makes sense for your symptom pattern, contact us so we can help you triage and choose a conservative-first plan that matches your severity.
Surgery, When It Makes Sense, and Why Many People Want To Avoid It
When people compare a steroid injection vs surgery, the biggest differences are risk, downtime and what happens if symptoms come back.
Surgery can be effective for the right person at the right time. But many people still want to avoid it unless clearly necessary.
Why Surgery Is Often a Last Step
Surgery is typically reserved for:
- Severe or progressive symptoms
- Constant numbness
- Weakness or frequent dropping
- Failure of conservative care when done consistently and correctly
Why Some People Regret Rushing Into Surgery
People can feel disappointed when:
- The diagnosis was not purely carpal tunnel, for example, neck or elbow nerve irritation was also present
- Nerve compression was present for too long, so numbness improves slowly or incompletely
- Postoperative sensitivity or stiffness limits early function
- The underlying drivers, like repetitive load, inflammation, or systemic contributors, were never addressed
A Simple Triage Checklist, Mild, Moderate, Severe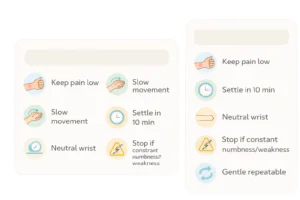

Use this checklist to see where you fall in the steroid injections vs splints vs surgery sequence.
Use this to understand what is typically tried first for your level.
Mild Pattern
- Tingling comes and goes
- Symptoms mainly at night or after long hand use
- No weakness, no constant numbness
Typical first steps:
- The Carpal Solution at night for the six-week protocol
- Ergonomic changes and microbreaks
- Gentle glides and stretching plan
Moderate Pattern
- Night waking is frequent
- Symptoms interfere with work or daily tasks
- Occasional dropping or clumsiness, but not clear weakness
Typical pathway:
- Conservative-first plan with tighter structure and tracking
- Consider injection if sleep and function do not improve
- Reassess quickly, do not drift for months without progress
Severe or Urgent Pattern
- Constant numbness
- Clear weakness, loss of grip strength, and frequent dropping
- Visible thumb muscle changes, or fast-worsening symptoms
Typical pathway:
- Prompt medical evaluation
- Conservative care may still play a role, but surgery discussion often happens sooner
- Do not delay if the function is declining
If you are not sure which category you are in, contact our team.
A Two-Week Decision Test You Can Run at Home

If you are in the mild-to-moderate range, this is a practical way to avoid estimation.
Week 1
- At night, use the Carpal Solution, and keep your wrists neutral with a pillow rather than a splint.
- During the day, reduce force and repetition, and add microbreaks every 30 to 45 minutes.
- Exercises: do gentle tendon and nerve glides once or twice daily.
- Track two markers, nights waking from symptoms, and minutes of comfortable work before tingling begins.
Week 2
- Keep the same plan.
- Make one ergonomic upgrade: mouse position, keyboard height, tool grip, and phone scrolling habits.
- If night waking is clearly improving, you are on the right track: finish the six-week protocol and keep the exercise plan.
- If there is little change, it is time to compare next steps, including therapy support or injection discussions.
Common Mistakes That Lead to Unnecessary Escalation
These mistakes push people from splints to injections to surgery faster than they need to, and they can turn a cortisone shot vs surgery carpal tunnel decision into a rushed one.
- Trying three devices at once, then not knowing what helped
- Wearing rigid support all day, then getting stiff and weaker
- Doing aggressive stretches that spike tingling, then giving up on movement entirely
- Waiting too long with constant numbness or weakness
- Treating the injection as a “cure”, then returning to the same overload pattern
The goal is not “never escalate,” the goal is “escalate only when the conservative-first plan has been done well, and outcomes are clear.”
Questions to Ask Before an Injection or Surgery
Before you say yes to a cortisone shot or an operation, these questions help you and your doctor make the right call:
- What is causing my symptoms, and how sure are we that it is carpal tunnel syndrome?
- Have I tried a well-reviewed conservative treatment for at least 12 weeks?
- How long does relief from an injection usually last, and how many can I safely have?
- What are the risks of surgery for someone with my health history, including diabetes, thyroid conditions or arthritis?
- How much time off work will I need, and what if symptoms remain or come back?
Carpal tunnel surgery has a patient satisfaction rate lower than 69%, because about 31% of patients report lingering or recurring symptoms, and no patient is satisfied with lingering symptoms. For a longer list, see questions to ask your doctor.
Before you choose between injections, splints and surgery, check whether you are in a group that should avoid surgery: Who Should Avoid Carpal Tunnel Surgery? Inflammatory Conditions and Other Red Flags.
When To Contact Our Team
Reach out if you want help choosing what to try first based on your symptoms and lifestyle, especially if:
- Sleep interruption is ongoing
- You are dropping objects or losing grip confidence
- You are unsure whether you are mild, moderate, or severe
- You want to avoid unnecessary invasive steps and follow a conservative-first plan
When Healing Needs a Doctor’s Help and Professional Medical Evaluation
- Constant numbness that does not improve or loss of feeling in the fingertips that does not improve in 4 to 8 weeks.
- Extreme loss of the muscle at the base of the thumb, with loss of grip strength that does not improve over 6 to 8 weeks.
- Worsening symptoms over 6 to 8 weeks while using the best conservative treatments
- Symptoms that begin suddenly after hand or wrist trauma, a fracture or severe sprain from a fall or auto accident.
- Odd Symptoms that are not consistent with the Carpal Tunnel Symptoms listed on this website, that might be indicative of other nerve issues. A nerve conductivity study can clear up the confusion with minimal costs and not too much pain and no risk.
These signs may mean more advanced nerve involvement or a different condition and deserve professional medical evaluation and in person consultation. Home treatment can be used alongside professional in-person medical care while you wait for the healthcare delivery system to fit you into their schedule. There is no reason to wait doing nothing. You can start proven natural conservative treatment with good patient reviews while you wait for your appointments. If your symptoms start improving over 6 to 8 weeks, then you know you are on the right track and surgery is not necessary.