Created by renowned Harvard health care professionals.


A cortisone injection for carpal tunnel syndrome can temporarily reduce swelling around the median nerve and ease numbness, tingling, and pain. Relief may last weeks or months, but injections do not reliably provide lasting improvement. They are often considered for mild to moderate symptoms, alongside a plan to monitor nerve function and prevent worsening.


Introduction
Can a cortisone injection for carpal tunnel relieve symptoms? Yes. A corticosteroid shot into the wrist can reduce irritation around the median nerve and provide meaningful short-term symptom relief, although it is not a dependable long-term cure.
If tingling fingers or numbness in the hand are waking you at night, you may be weighing a shot against a splint, at-home care, or surgery. This guide to carpal tunnel treatment explains what the injection does, how long its benefits may last, what risks to discuss, and when symptoms call for a more definitive treatment.
What Is a Cortisone Injection for Carpal Tunnel?
Carpal tunnel syndrome develops when the median nerve is compressed as it travels through a narrow passage on the palm side of your wrist. Common symptoms include tingling or numbness in the thumb, index, middle, and part of the ring finger, along with night discomfort, weakness, or difficulty gripping.
A cortisone injection for carpal tunnel, also called a corticosteroid or steroid injection, places an anti-inflammatory medication near the nerve inside the carpal tunnel. Reducing swelling can lower pressure and improve symptoms. It does not physically make the tunnel larger.
If you are new to the condition, start with our explanation of carpal tunnel syndrome.
How Effective Are Cortisone Shots, and How Long Do They Last?
How effective is a cortisone injection for carpal tunnel? A 2023 Cochrane review found that local corticosteroid injections probably improve symptoms and hand function in people with mild to moderate carpal tunnel syndrome. Benefits were observed for up to six months in the available studies, although individual responses varied.
That finding is compatible with the 2024 American Academy of Orthopaedic Surgeons (AAOS) clinical practice guideline, which concludes that injections do not provide reliable long-term improvement. In other words, a treatment can help for several months without being a lasting fix.
A shot may be particularly useful when nighttime symptoms interrupt sleep or when you need short-term relief while discussing the next step. It is less reassuring when numbness becomes constant or hand strength is declining. Do not judge success by pain relief alone.
Who Should Consider a Cortisone Injection for Carpal Tunnel?
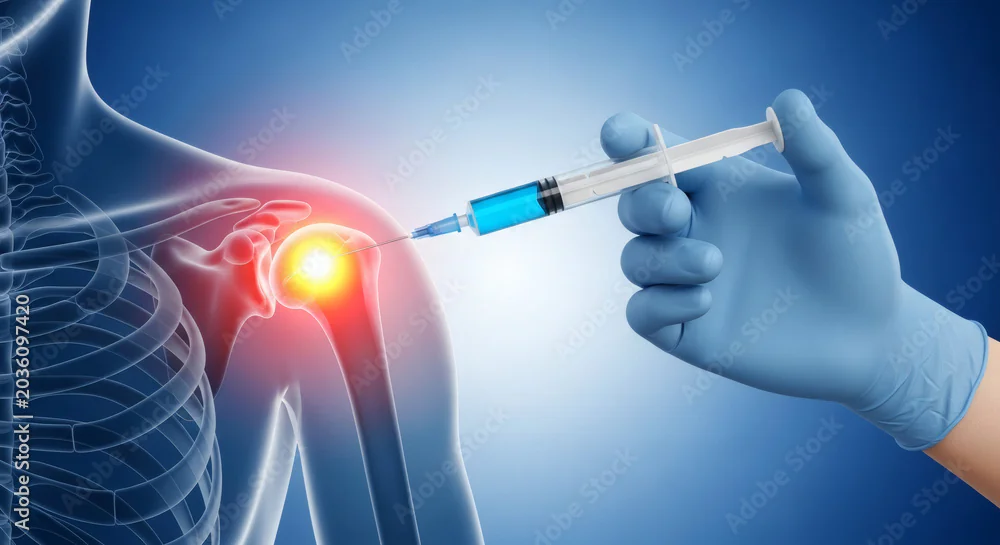
A cortisone injection for carpal tunnel may be reasonable if you have a clinician-confirmed diagnosis, mild or moderate symptoms, and an informed preference to try a nonsurgical approach. It may also be considered when a properly fitted night splint has not provided enough relief, which is also how the NHS describes the usual order of treatment.
Ask for further evaluation before relying on another injection if you have:
- Constant or progressively worsening numbness.
- Weakness when pinching or gripping, or frequent dropping of objects.
- Visible shrinking of muscles at the base of the thumb.
- An uncertain diagnosis, especially if symptoms involve the little finger or extend from the neck.
Seek prompt medical assessment for new or worsening weakness or persistent loss of feeling. Delaying evaluation when nerve damage is developing can reduce the opportunity for recovery. For a quick overview of what to watch for, see our guide to numbness in the hand and other symptoms.
What Happens Before, During, and After the Injection?
- Confirm the diagnosis and treatment goal. Your clinician reviews the symptom pattern and examines your hand. Additional testing may be appropriate when the diagnosis or severity is unclear. Expected outcome: a reasoned decision about whether a shot fits your condition. Pitfall: treating every form of hand numbness as carpal tunnel syndrome.
- Review medical conditions and medicines. Mention diabetes, prior injection reactions, active infection, blood-thinning medicines, and pregnancy. Expected outcome: a plan tailored to your risks. Pitfall: stopping prescribed medication on your own before the procedure.
- Receive the injection. The clinician cleans the skin and injects corticosteroid, sometimes with a local anesthetic. Ultrasound guidance may be used to help position the needle. Expected outcome: medication delivered near the affected nerve. Pitfall: ignoring a sharp, electric-shock sensation during injection. Tell the clinician immediately.
- Follow aftercare instructions. Temporary soreness can occur. Your clinician may recommend easing off strenuous gripping briefly and monitoring the injection site. Expected outcome: a comfortable return to normal activities. Pitfall: assuming immediate anesthetic relief means the steroid’s full effect has arrived.
- Review the result. Record symptoms over the following days and weeks and arrange follow-up if improvement is limited or symptoms return. Expected outcome: a clear decision on continuing conservative care or seeking specialist advice. Pitfall: repeating injections without reassessing worsening weakness.
Cortisone Injection for Carpal Tunnel: Risks, Side Effects, and Warning Signs
Possible effects of a cortisone injection for carpal tunnel include short-lived pain, swelling, or a temporary flare of discomfort at the wrist. Less common problems include infection, skin or fat changes at the injection site, and injury to a nerve or tendon. Steroid medication can temporarily raise blood glucose, which matters for people with diabetes. The evidence review found serious complications to be uncommon, but reporting across studies was incomplete.
Contact your treating clinician promptly for increasing redness, warmth, swelling, or worsening pain after an injection. Seek urgent care for fever with an increasingly painful injection site, or a sudden major change in hand sensation or strength.
Cortisone Injection vs. Other Carpal Tunnel Treatments
How does a cortisone injection for carpal tunnel compare with the other options? The table summarizes the main differences.
| Option | Best For | Key Features | Limitations |
|---|---|---|---|
| Night wrist splint | Mild symptoms, especially at night | Holds the wrist closer to neutral during sleep | May take weeks to help; does not solve every case |
| Cortisone injection | Short-term relief in selected mild to moderate cases | Anti-inflammatory medication delivered at the wrist | Symptoms may return; no reliable long-term benefit |
| Activity adjustments and guided therapy | Reducing aggravating positions and improving hand use | Changes technique, pacing, and symptom management | Evidence varies by intervention; not a substitute for evaluating weakness |
| Carpal tunnel release surgery | Persistent, severe, or progressive nerve compression | Releases the ligament to reduce nerve pressure | Procedure and recovery involve risks and downtime |
Night splinting and steroid injections are established nonsurgical options, while surgery directly relieves nerve compression. The right choice depends on symptom severity, hand function, prior treatment response, and personal priorities. You can read more about night splints and braces, about carpal tunnel release surgery, and about the typical order in which these are tried in our guide to steroid injections vs. splints vs. surgery.
A Practical Framework for Choosing Your Next Step
Use the RELIEF framework as a discussion aid when considering a cortisone injection for carpal tunnel, not as a substitute for a diagnosis.
- R, Recognize severity: Are symptoms occasional, frequent, or constant?
- E, Evaluate function: Is grip strength, thumb movement, or dexterity changing?
- L, Look at what worked: Did a neutral wrist splint or earlier injection help, and for how long?
- I, Identify your goal: Do you need short-term comfort or a lasting solution to progressive compression?
- E, Examine risks: Discuss diabetes, medication use, infection, and procedure concerns.
- F, Follow up: Set a checkpoint to review symptoms rather than waiting indefinitely.
Use this framework when comparing reasonable choices for mild or moderate, confirmed carpal tunnel syndrome. Do not use it to delay care for constant numbness, worsening weakness, or possible muscle wasting. In those situations, an examination takes priority.
How to Track Whether Treatment Is Helping

Two simple measures can help:
- Nighttime waking reduction (%) = (baseline wake-ups − current wake-ups) ÷ baseline wake-ups × 100. For example, going from four disturbed nights each week to two is a 50% reduction.
- Symptom-free day rate (%) = symptom-free days ÷ days tracked × 100. For example, five symptom-free days in a 14-day diary equals about 36%.
These are tracking examples, not promises or clinical trial results. If pain improves but constant numbness or weakness remains, get reassessed.
Example: Choosing Short-Term Relief Without Losing Sight of Nerve Health
Illustrative scenario, not a real patient or a treatment outcome: A person with nighttime thumb and index-finger tingling has an examination consistent with mild carpal tunnel syndrome. A neutral wrist splint helps somewhat, but sleep remains disrupted.
After discussing risks and expectations, the person chooses a cortisone injection for carpal tunnel for possible short-term relief. They also keep a symptom diary and arrange a follow-up visit. If symptoms recur, they plan to review the diagnosis, hand function, and whether a specialist assessment is appropriate. The important decision is not simply whether the injection helps today, but whether the nerve remains healthy over time.
Key Takeaways
- A cortisone injection for carpal tunnel can ease symptoms temporarily, especially in mild to moderate cases.
- Benefits may last for months, but long-term improvement is not reliable.
- Splints, activity changes, injections, and surgery address different needs.
- Persistent numbness, worsening grip, or thumb weakness warrants medical assessment.
- Track function as well as pain, and agree on a follow-up plan before the shot.
- Repeated injections should prompt a fresh discussion of longer-term options.
Frequently Asked Questions
Do cortisone injections work for carpal tunnel syndrome?
Yes, a cortisone injection for carpal tunnel syndrome can reduce numbness, tingling, and pain, especially in mild or moderate cases. Research supports short-term relief, but the benefit may fade. An injection reduces swelling around the median nerve; it does not permanently enlarge the carpal tunnel.
How long does a carpal tunnel cortisone shot last?
Relief varies. Some people improve for weeks, while others notice benefit for several months. A Cochrane review found improvement in symptoms and hand function lasting up to six months in studied groups. Symptoms can return earlier, and a shot should not be assumed to provide permanent relief.
How quickly does a cortisone shot start working?
A local anesthetic, if used, may briefly numb the area right away. The corticosteroid itself often takes several days to have a noticeable effect. Your clinician can explain the expected timeline for the medication used. Call the clinic if pain is worsening rather than gradually settling.
Is a cortisone injection for carpal tunnel painful?
You may feel a needle pinch, pressure, or brief discomfort during the injection. Tenderness afterward is possible. Clinicians use careful placement to avoid irritating the median nerve and nearby structures. Tell your clinician immediately if you feel an electric-shock sensation during the procedure.
Can a cortisone injection cure carpal tunnel permanently?
It usually should not be considered a permanent cure. A corticosteroid can reduce swelling and relieve pressure temporarily, but it does not release the ligament that forms the roof of the tunnel. The American Academy of Orthopaedic Surgeons reports no reliable long-term improvement from corticosteroid injections.
How many cortisone injections can I get for carpal tunnel?
There is no universal number that is appropriate for everyone. Whether to repeat an injection depends on your previous response, symptom severity, other medical conditions, and the risks of additional treatment. If symptoms repeatedly return, ask whether further testing or a surgical consultation would be more useful than another shot.
Are carpal tunnel steroid shots safe for people with diabetes?
A person with diabetes may still be considered for an injection, but corticosteroids can temporarily raise blood glucose. Tell the clinician who manages your diabetes before the procedure and ask whether extra monitoring is needed afterward. Treatment choices also depend on infection risk, symptom severity, and how well glucose levels are controlled.
Should I wear a wrist splint after a cortisone injection?
Your clinician may recommend continuing a neutral-position wrist splint at night, particularly if sleeping with a bent wrist triggers symptoms. A splint and an injection serve different purposes: the splint limits positions that increase nerve pressure, while the injection reduces local inflammation. Follow any specific post-injection instructions.
Is a cortisone shot better than carpal tunnel surgery?
Neither is automatically the better choice. A cortisone injection for carpal tunnel is less invasive and may make sense for short-term relief in mild or moderate cases. Surgery directly releases pressure on the nerve and is more often considered when symptoms persist, weakness develops, or nerve damage is suspected. Discuss severity and goals with a hand specialist.
What if my carpal tunnel symptoms come back after an injection?
Track when numbness, night waking, and loss of grip return, then arrange reassessment. Ask whether the diagnosis remains correct and whether symptoms indicate worsening nerve compression. Continuing weakness, constant numbness, or thumb muscle wasting deserves prompt medical attention rather than repeated short-term treatment.
Carpal Tunnel Treatment Glossary
- Carpal tunnel: The narrow passage in the wrist that contains the median nerve and flexor tendons.
- Median nerve: The nerve responsible for sensation in several thumb-side fingers and movement of some thumb muscles.
- Corticosteroid: A medicine that reduces inflammation and can ease nerve compression symptoms.
- Local anesthetic: A medicine that temporarily numbs an area during or around a procedure.
- Nerve conduction study: A test that measures how well electrical signals travel through a nerve.
- Ultrasound guidance: Imaging used to see tissues and help guide needle placement.
- Night splint: A wrist support intended to limit positions that aggravate symptoms during sleep.
- Thenar atrophy: Shrinking of the muscle area at the base of the thumb, which can signal advanced nerve involvement.
- Carpal tunnel release: Surgery that divides the transverse carpal ligament to reduce pressure on the median nerve.
- Symptom recurrence: The return of numbness, pain, or tingling after a period of improvement.
Conclusion: Make Cortisone Relief Part of a Longer-Term Plan
A cortisone injection for carpal tunnel can provide welcome relief from symptoms, but its value lies mainly in the short term. Ask your clinician whether a shot fits your symptom severity, how you will measure improvement, and what should happen if relief fades. Protecting hand strength and sensation matters more than repeatedly masking symptoms.
To compare every option side by side, see our overview of carpal tunnel treatment options or return to the main carpal tunnel treatment page.
Sources
- Local corticosteroid injection versus placebo for carpal tunnel syndrome. Cochrane Database of Systematic Reviews, 2023.
- Management of Carpal Tunnel Syndrome: Evidence-Based Clinical Practice Guideline. American Academy of Orthopaedic Surgeons, 2024.
- Carpal tunnel syndrome: treatment. NHS.
- Carpal Tunnel Syndrome. AAOS OrthoInfo patient guide.